

STORM-PE
Randomized Controlled Trial
First-of-its-kind RCT for acute intermediate-high risk pulmonary embolism (PE).
CAVT™ – Proven by Level 1 Evidence1


In Collaboration with
The PERT Consortium

Met Primary Endpoint

Prospective, Randomized Trial
Acute, Intermediate-High Risk PE
22 US & International Sites

100 Participants
Evaluate the efficacy and assess safety of treating acute, intermediate-high risk pulmonary embolism with anticoagulation alone versus anticoagulation plus computer assisted vacuum thrombectomy (CAVT) with the Indigo™ Aspiration System.
- Change in RV/LV ratio assessed by CTPA at 48-hoursa
- Major adverse events within 7 daysb
- Safety (symptomatic PE recurrence, all-cause mortality and PE-related mortality) as well as functional outcomes and quality of life assessments at 90 days
a. Results adjudicated by a blinded, independent imaging Core Lab
b. Major adverse event is defined as a composite of clinical deterioration requiring escalation of care, PE-related mortality, symptomatic recurrent PE, or major bleeding.
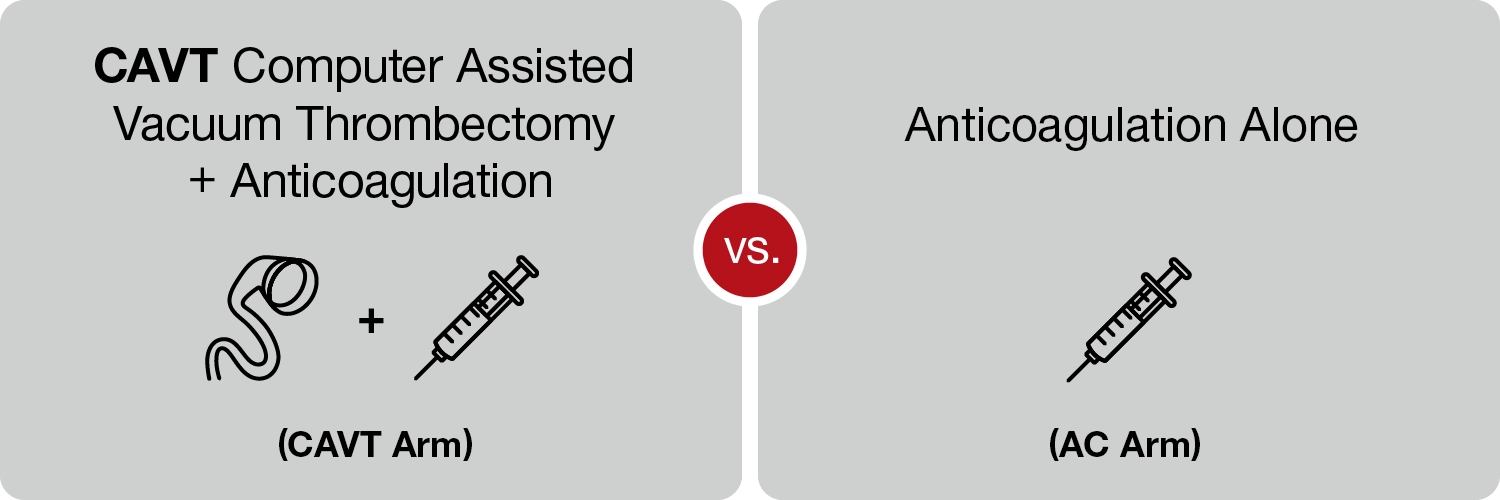
STORM-PE patients were randomized 1:1, divided into the computer assisted vacuum thrombectomy (CAVT) plus anticoagulation arm or the anticoagulation alone arm.
- Symptom onset of 14 days or less
- Acute PE with proximal filling defect confirmed by CTPA
- Intermediate-high risk PE demonstrated by RV/LV ratio and elevated biomarkers

Initial Results Now Published in American Heart Association Journal: Circulation
Trial Design Manuscript Published in American Heart Journal
ClinicalTrials.gov Study Site
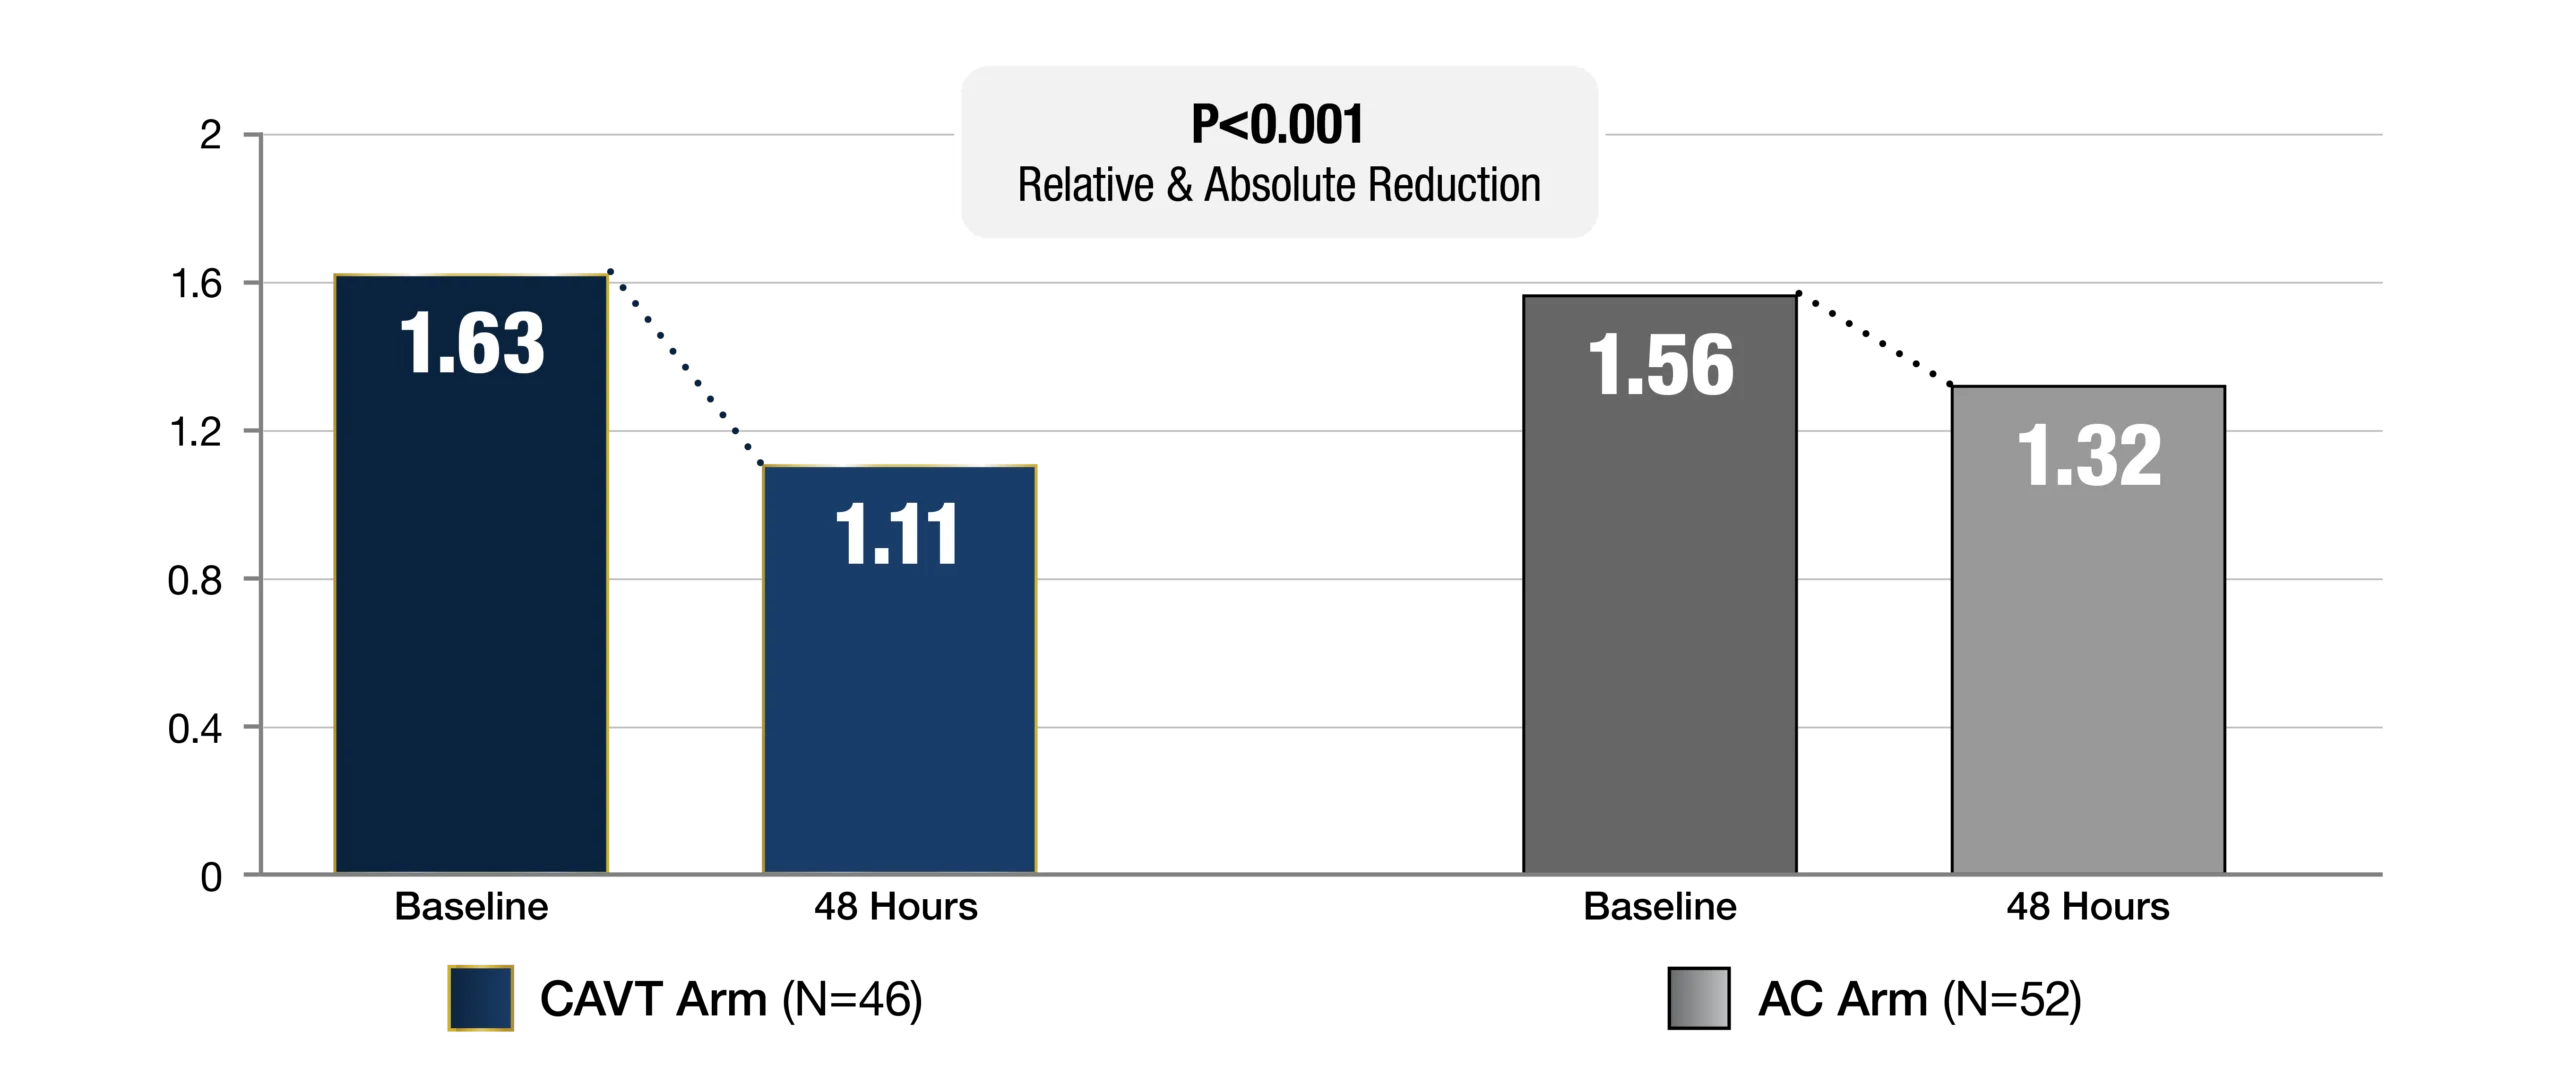
Primary Endpoint
RV/LV Reduction Baseline to 48 Hours
CAVT arm demonstrated a superior reduction in right heart strain (ΔRV/LV ratio) compared to AC alone

Safety Endpoint
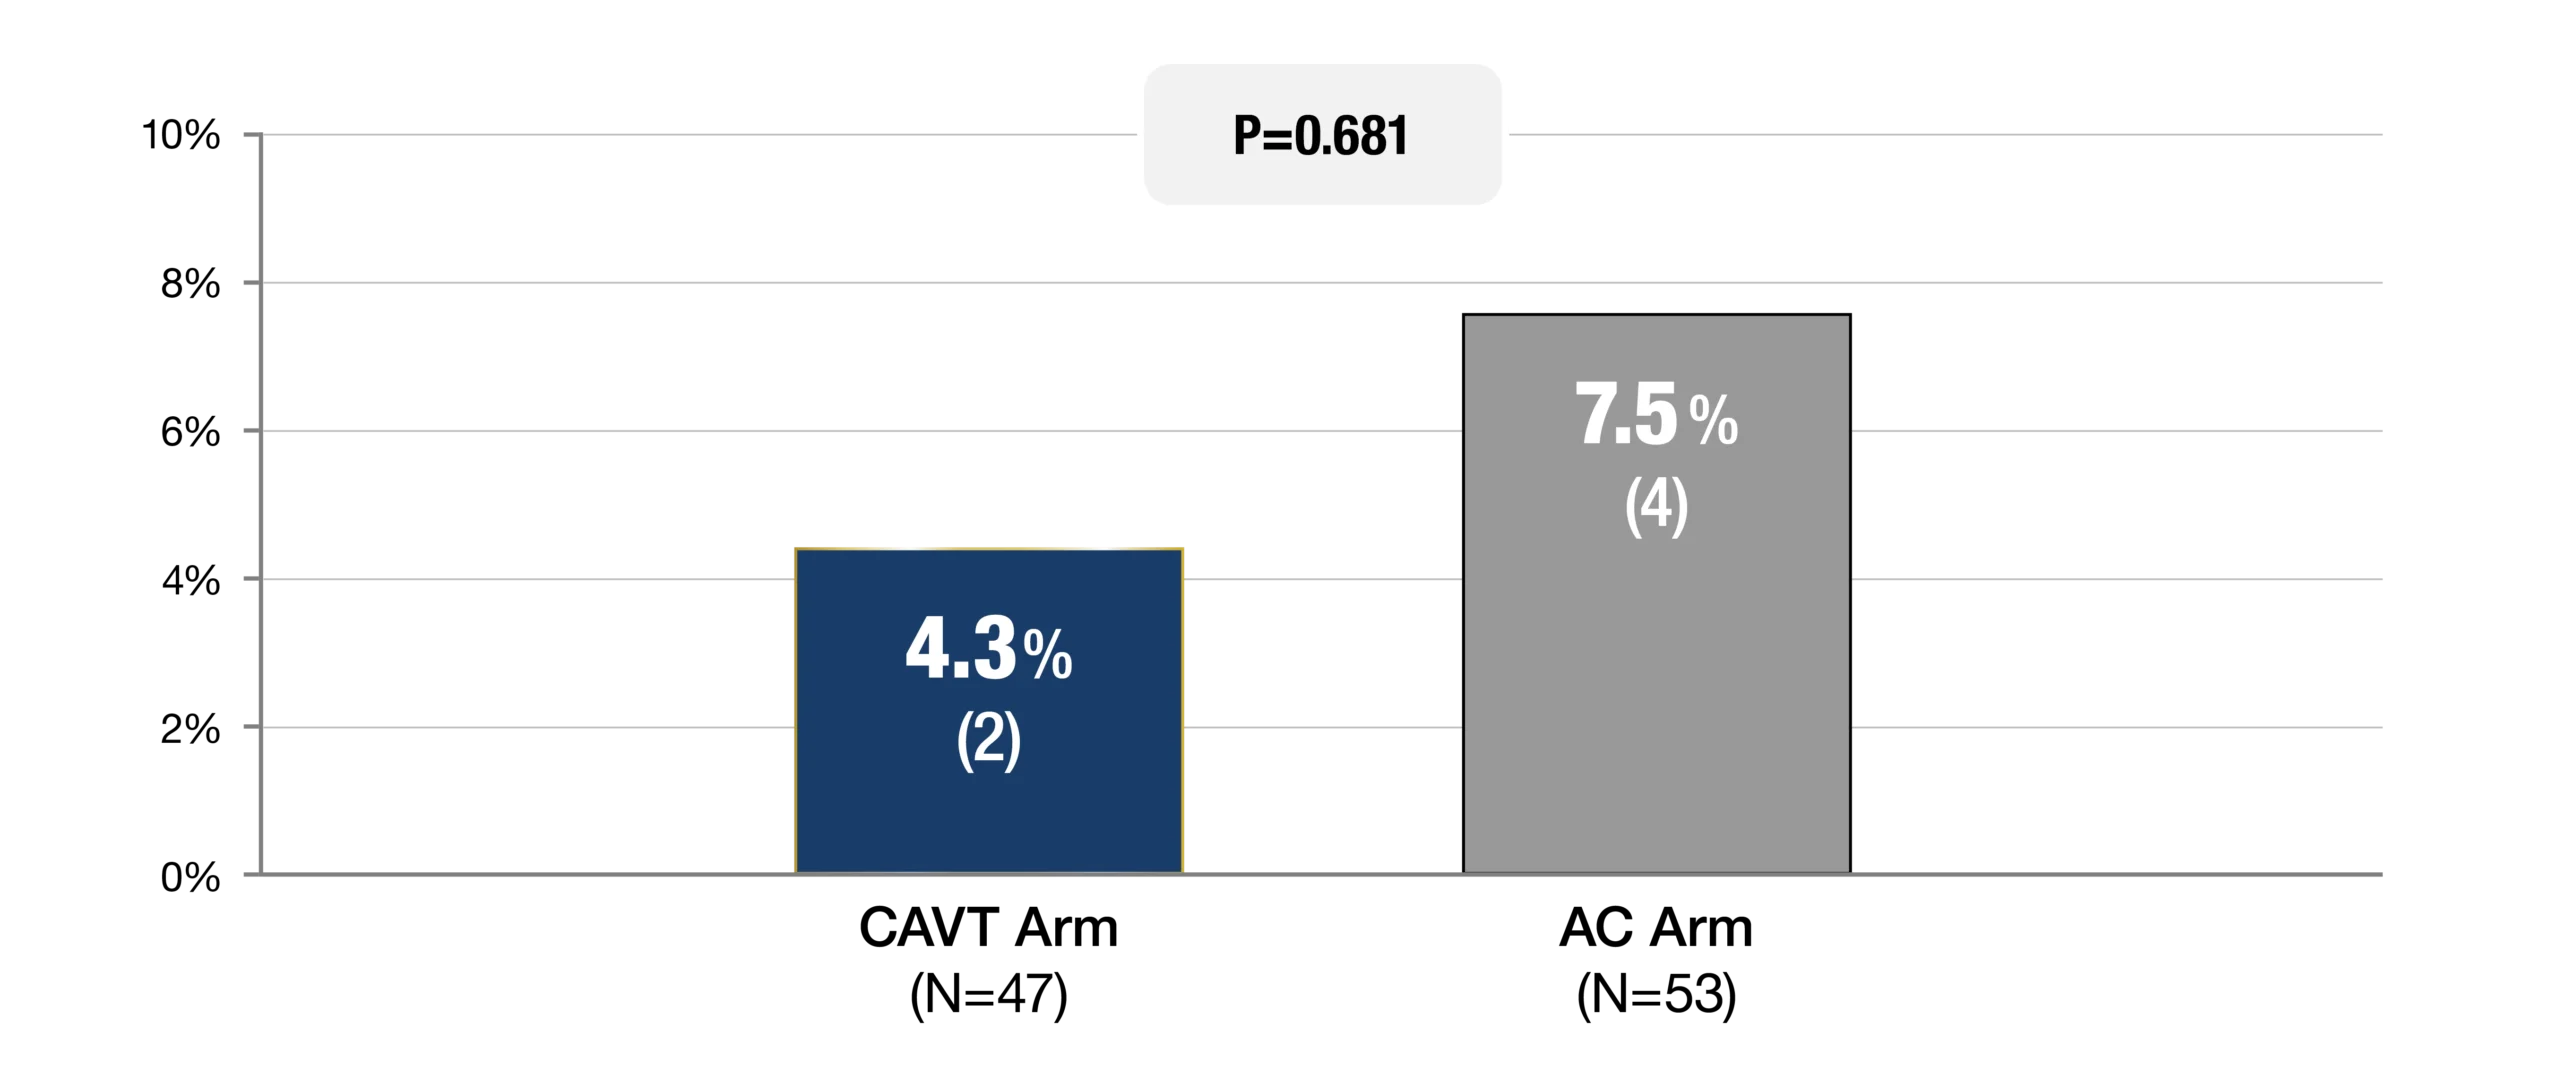
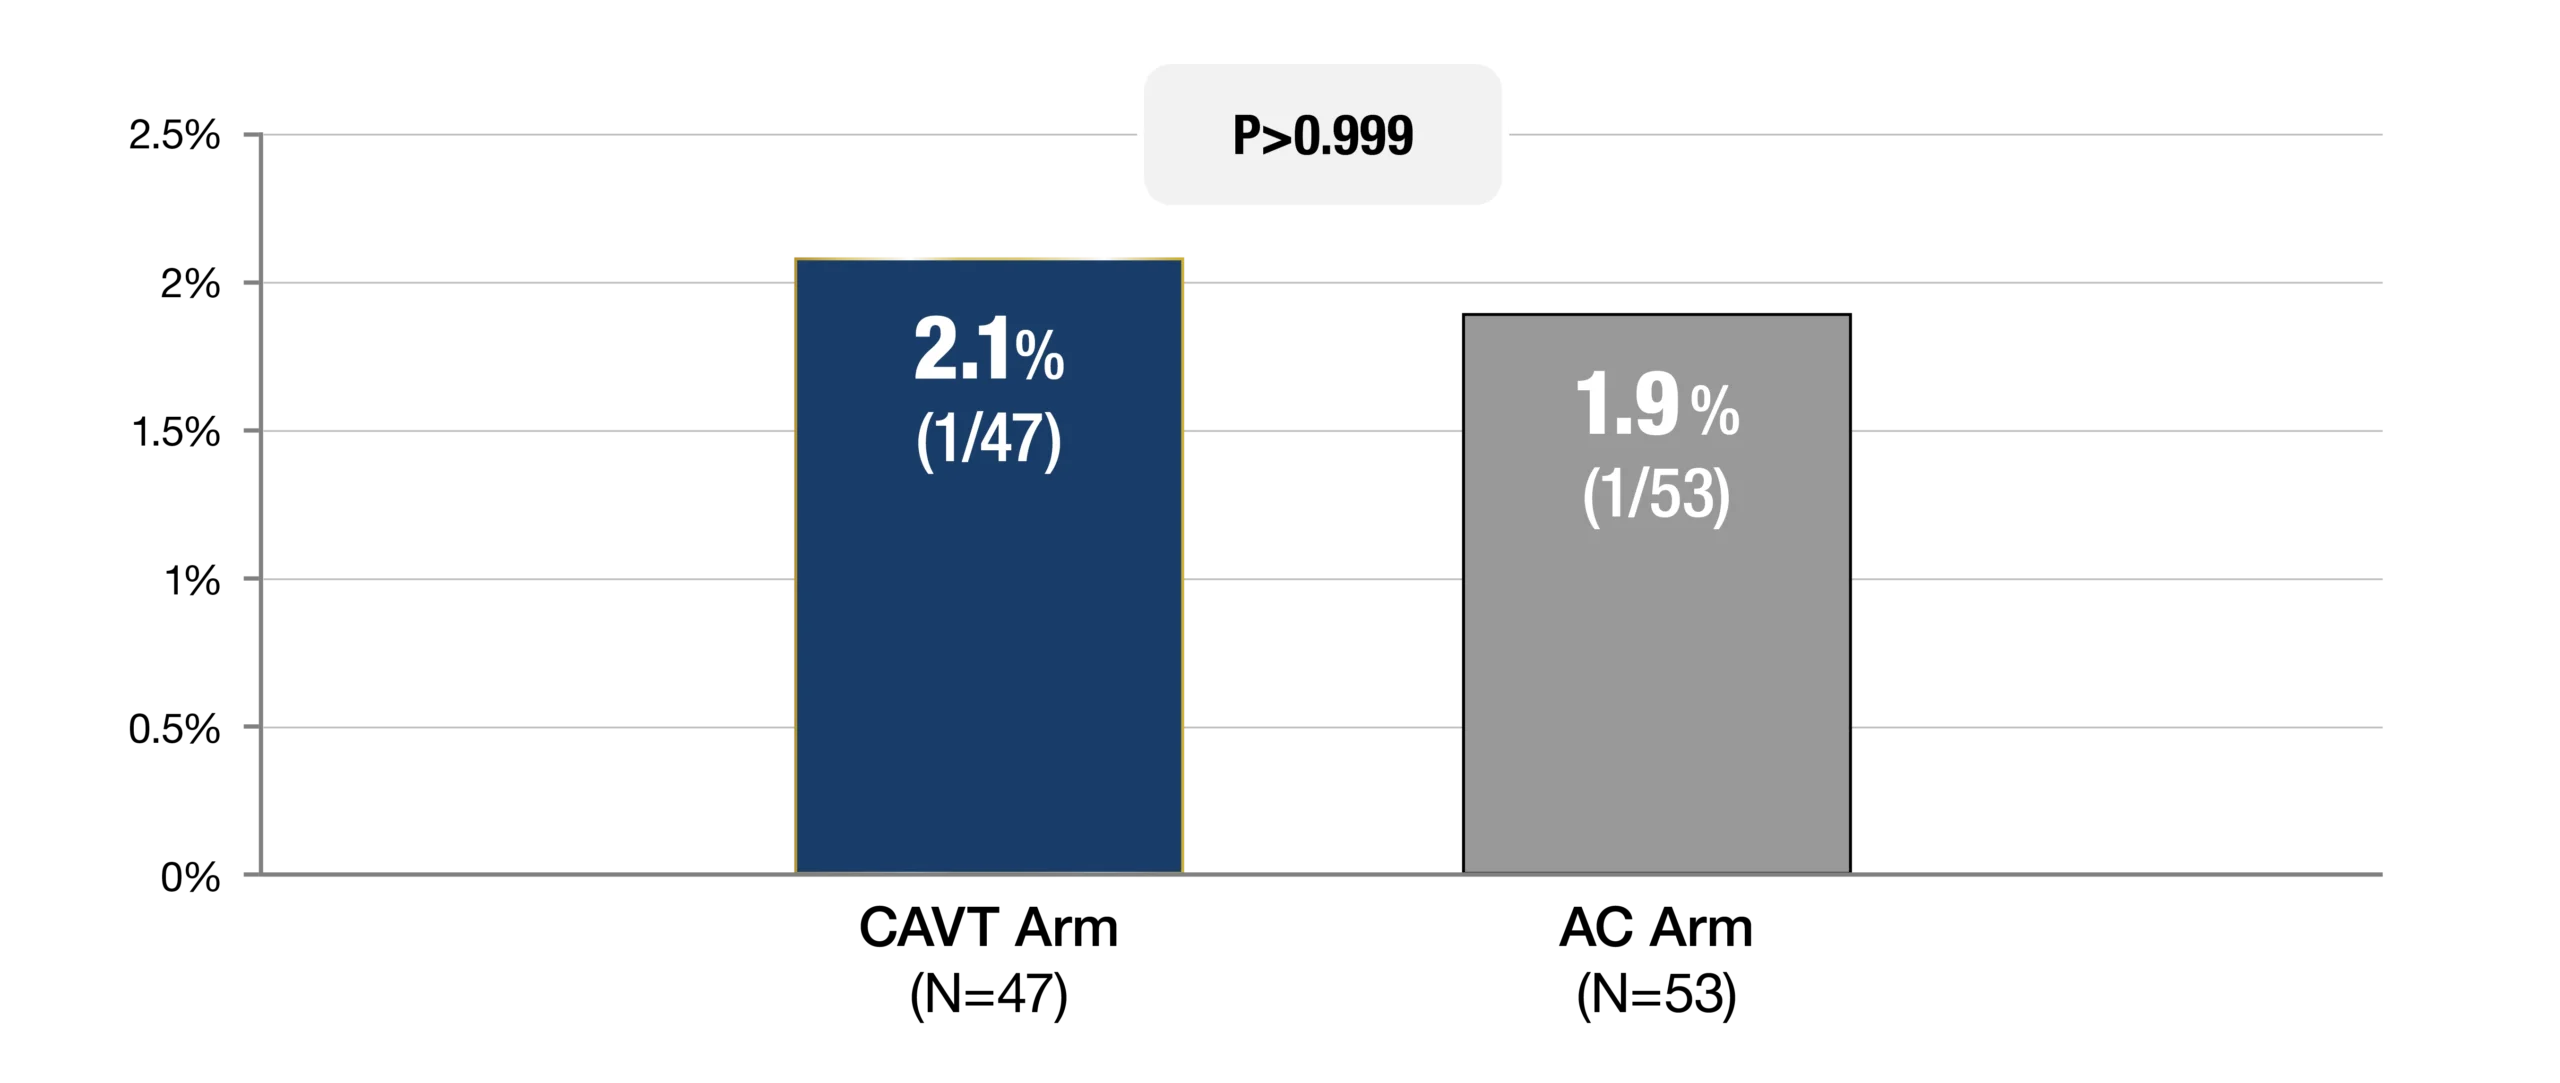
CAVT arm showed comparable safety rate to AC alone, with numerically fewer Major Adverse Event (MAE) in the CAVT armc
Composite MAE ≤ 7 Days (%, n)
Major Bleeding (BARC 3a-5)d
Procedure Data
Device Time (median)
25 min
[15.0, 41.0]
Procedure Time (median)
56 min
[42.0, 69.0]
mPAP Reduction (mean)
27.3%
(8.2 mmHg)
Technical
Successh
100%
(47/47)
Device Related Transfusion
0%
(0/47)
Clinical Outcomes
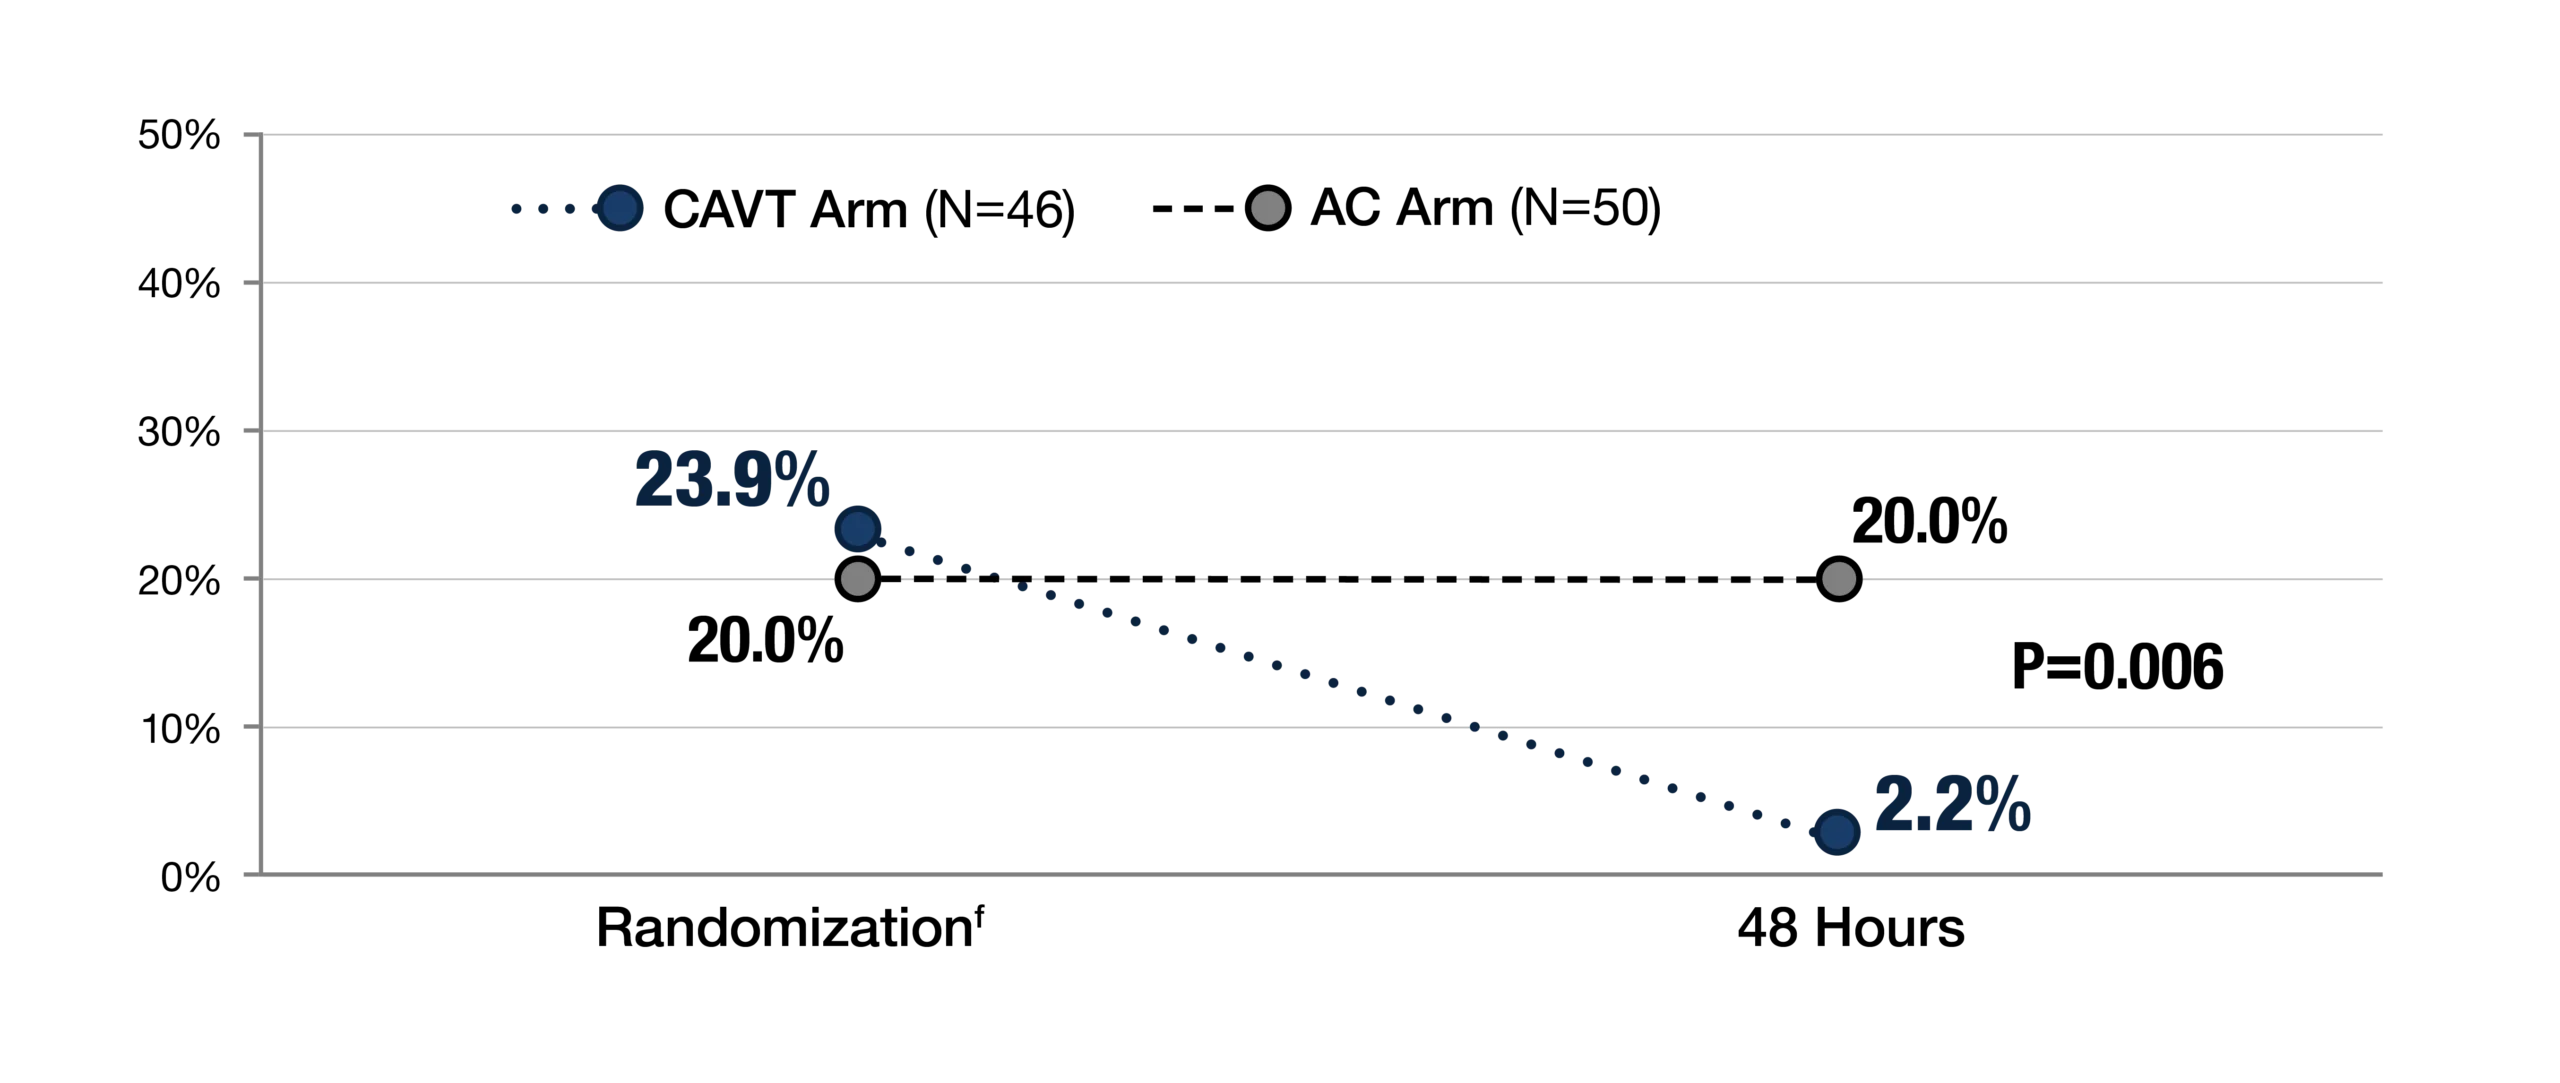
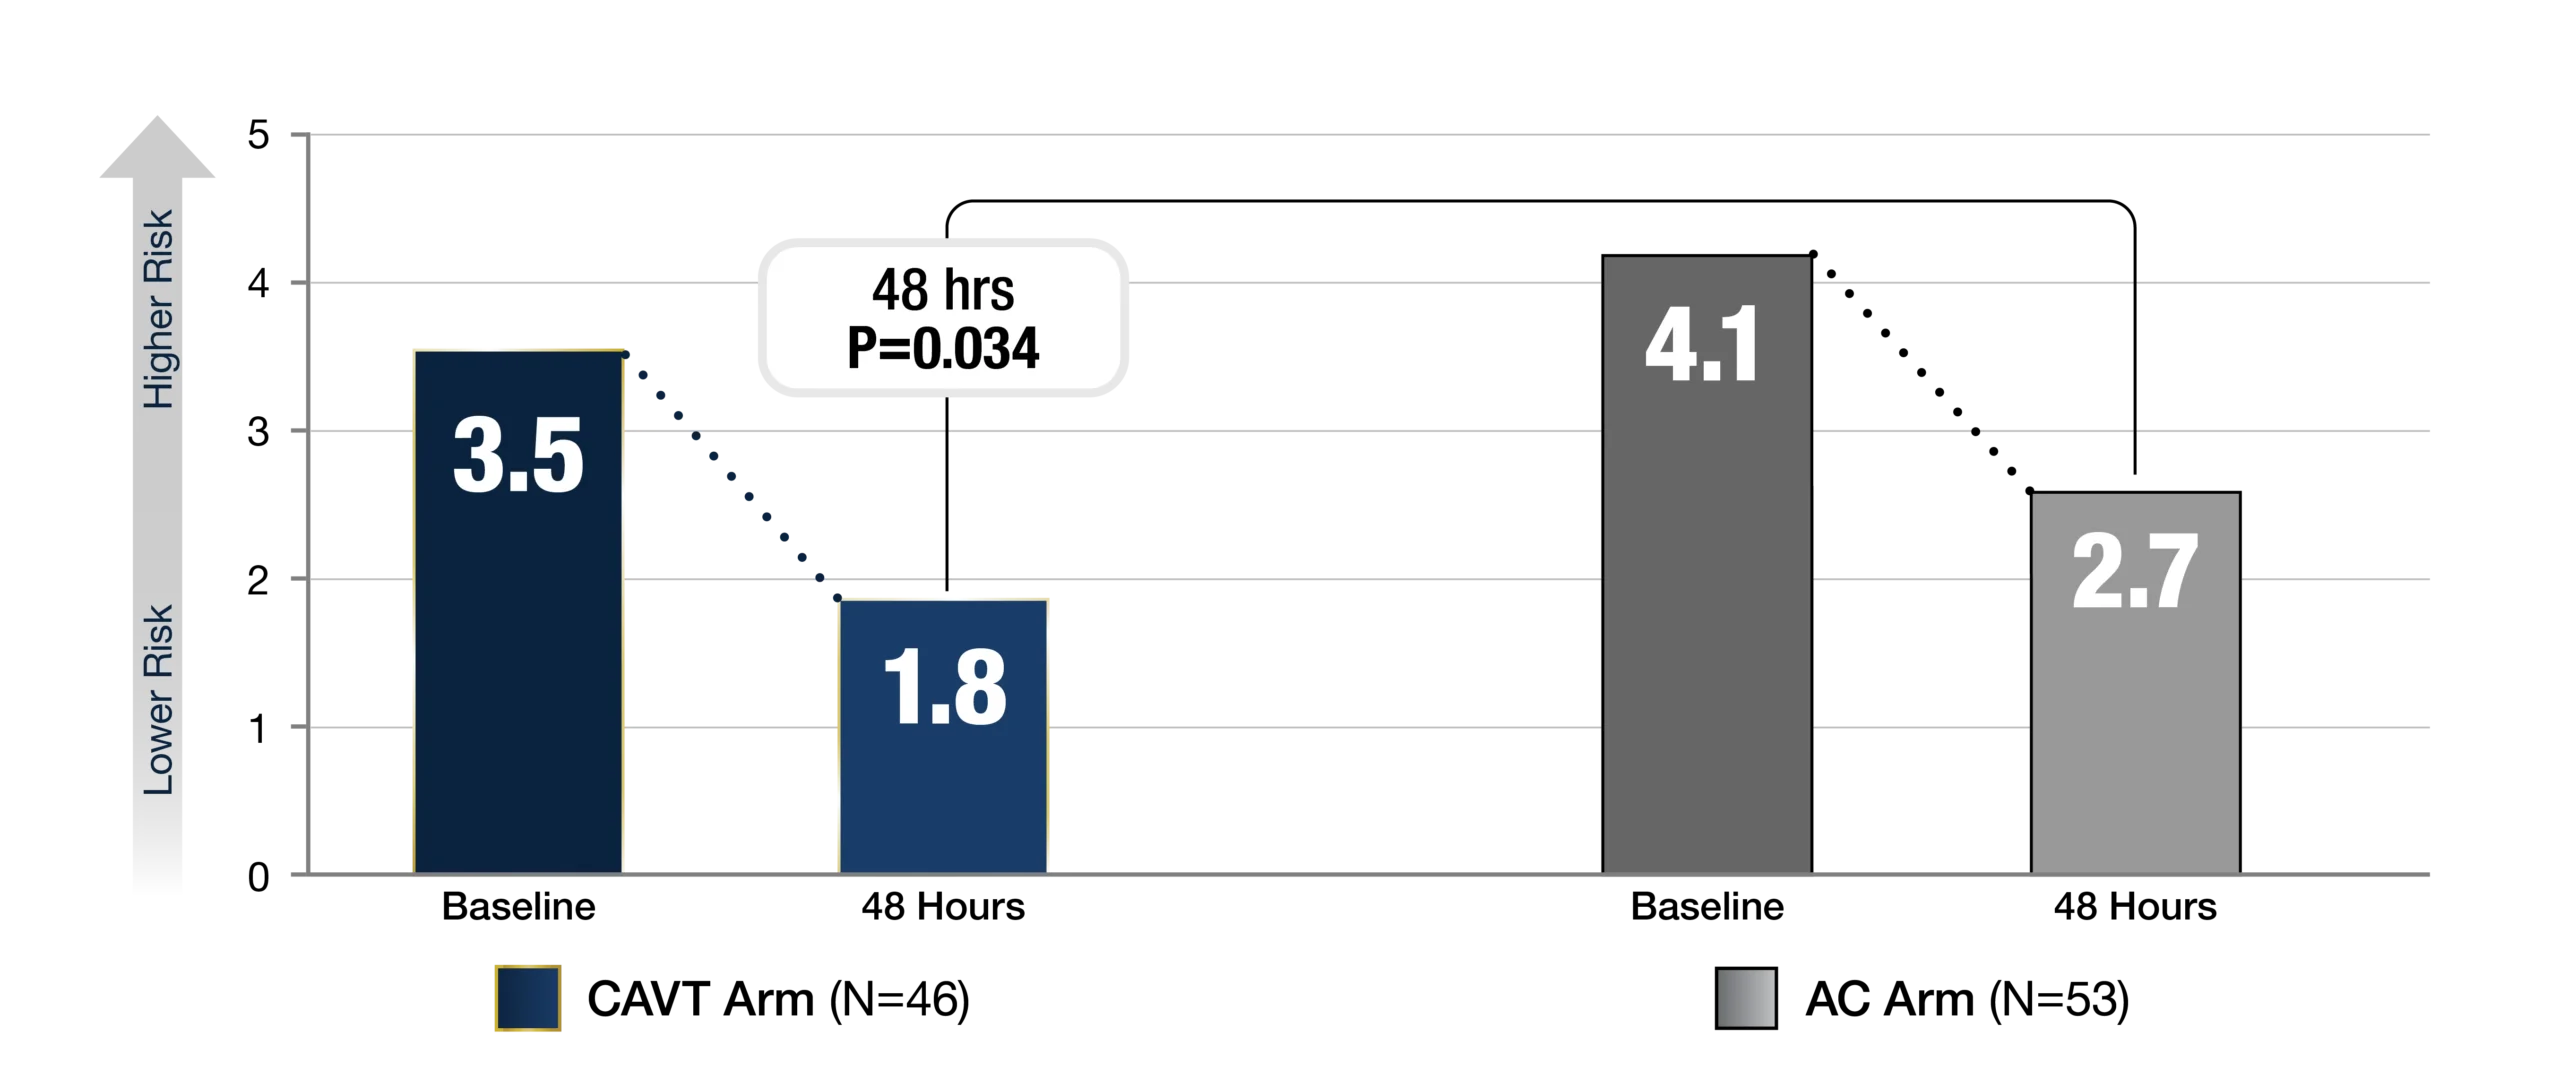
CAVT patients show earlier physiological recovery compared to AC arm
Tachycardia HR > 100 bpm, % of Patients
NEWS2 Score at Baseline & 48 Hours
90-Day Functional and QoL Outcomesc
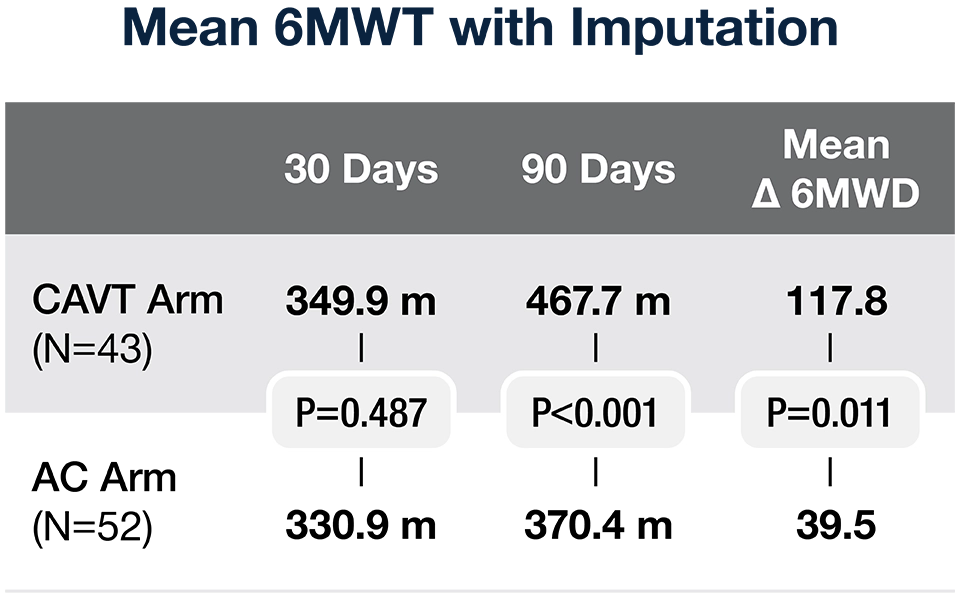
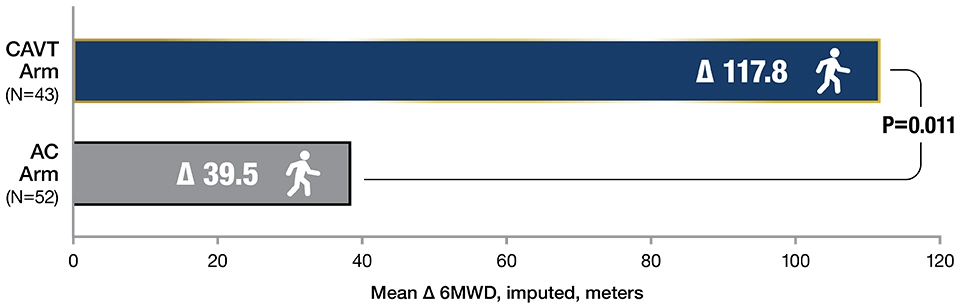
6-Minute Walk Test (6MWT) with Imputation3, g
With imputation, change in distance walked was 3-fold greater in CAVT patients
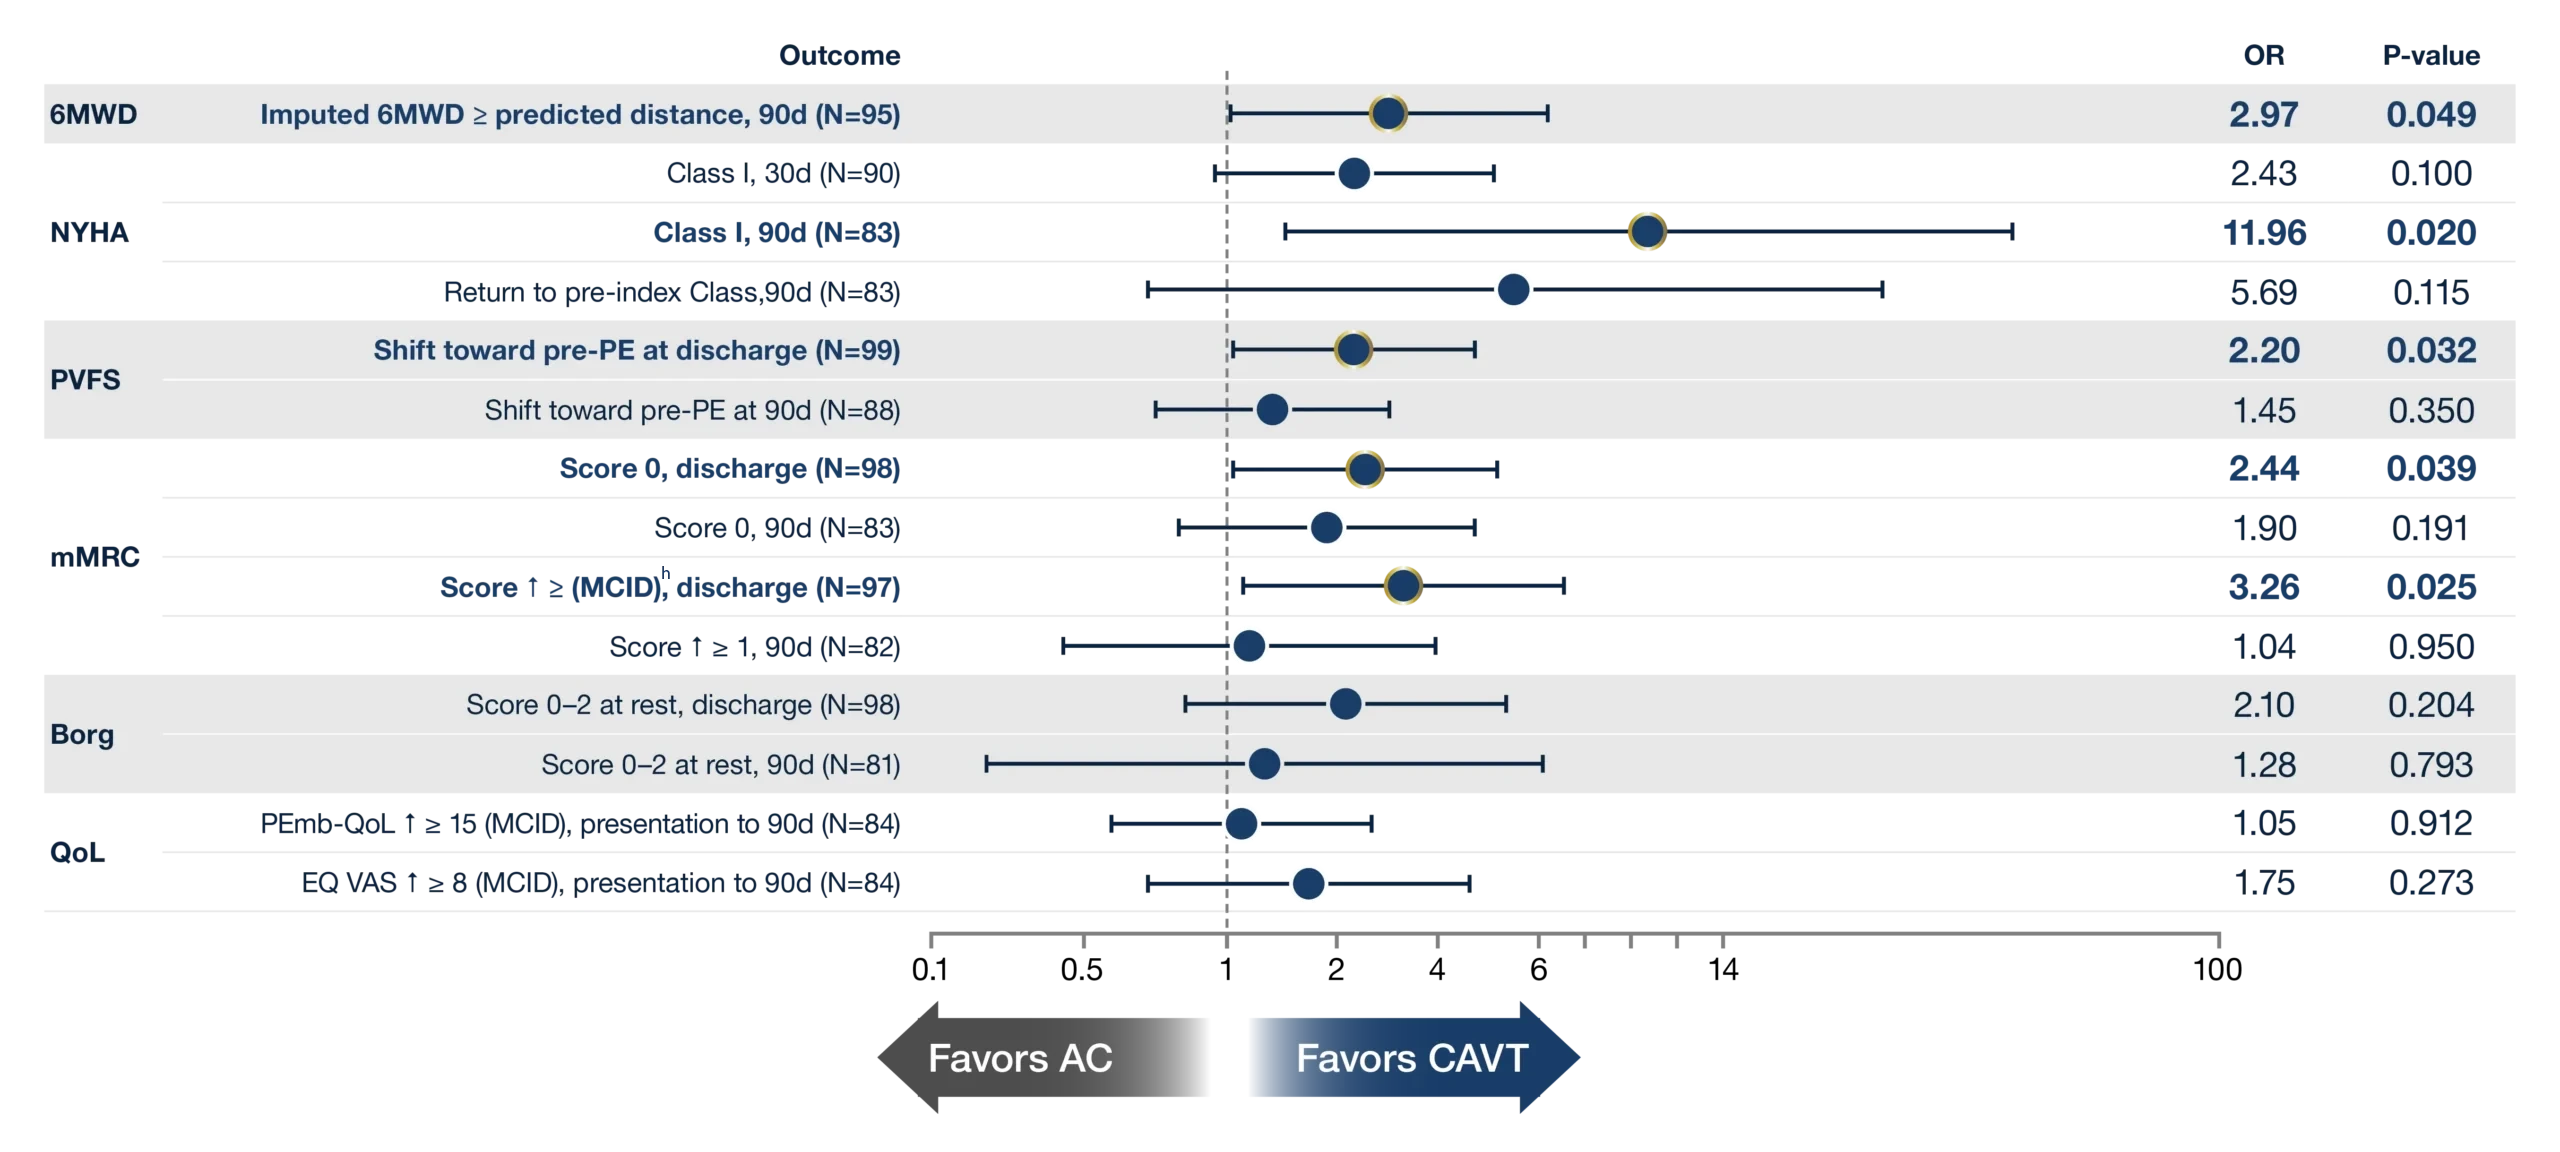
90-Day Outcomes Forest Plot
CAVT arm trended favorably for all functional and QoL outcomes measured in graphic below
National Principal Investigators
Rachel Rosovsky, MD
Hematology
Massachusetts General Hospital
Robert Lookstein, MD
Interventional Radiology
Mount Sinai Hospital
Steering Committee Members
Ido Weinberg, MD
Vascular Medicine
Massachusetts General Brigham
Richard Channick, MD
Pulmonology
UCLA Medical Center
John Moriarty, MD
Interventional Radiology
UCLA Medical Center
Sahil Parikh, MD
Interventional Cardiology
Columbia University Medical Center
Stavros Konstantinides, MD
Cardiology
University Medical Center Mainz
Suhail Dohad, MD
Interventional Cardiology
Cedars-Sinai Medical Center
Richard Davis
Patient Representative
1. Lookstein RA, Konstantinides SV, Weinberg I, et al. Randomized controlled trial of mechanical thrombectomy with anticoagulation versus anticoagulation alone for acute intermediate-high risk pulmonary embolism: primary outcomes from the STORM-PE trial. Circulation. 2026 Jan 6;153(1):21–34. doi:10.1161/CIRCULATIONAHA.125.077232.
2. Enright PL, Sherrill DL. Reference equations for the six-minute walk in healthy adults. Am J Respir Crit Care Med. 1998 Nov;158(5 Pt 1):1384–7. doi:10.1164/ajrccm.158.5.9710086.
3. Lookstein R. Clinical, functional, and quality of life outcomes through 90 days in the STORM-PE RCT for mechanical thrombectomy with anticoagulation vs anticoagulation alone in acute intermediate-high risk PE patients. Presented at:
Society of Interventional Radiology Annual Scientific Meeting (SIR 2026); 2026; Toronto, ON, Canada.
c. STORM-PE was powered for the primary endpoint only.
d. Type 3a was not considered major bleeding if it was related to an expected decrease in hemoglobin level due to fluid administration and if transfusion was less than 2 units.
e. Ability of catheter to access clot and perform aspiration.
f. Timepoint closest to randomization, after administration of AC and pre-procedure for the CAVT arm. Paired data represented.
g. Imputation was carried out separately by assigned randomized group and deaths were excluded.
h. MCID: Minimal Clinically Important Difference
STORM-PE demonstrated superiority to anticoagulation utilizing Lightning Flash™ 1.0 and 2.0. Efficacy was predefined as the difference between treatment arms in change of RV/LV ratio from baseline to 48 hrs. The clinical results presented herein are for informational purposes only, and may not be predictive for all patients. Individual results may vary based on patient specific-attributes and other factors.

Questions?
Contact us to learn more about our products and company